Why in News?
Nipah virus is back in Kerala. A 43-year-old man from Ramanattukara, on the southern edge of Kozhikode district, tested positive for Nipah, and the state has switched on the full outbreak protocol refined over six earlier episodes since 2018.
- The National Institute of Virology (NIV), Pune confirmed the infection on 11 June 2026 after the Kozhikode Medical College laboratory returned an initial positive.
- The patient cleaned old buildings and is suspected to have been exposed while clearing a disused, bat-infested structure near Feroke.
- He is critical and on ventilator support in an isolation ward at Kozhikode Medical College Hospital.
- Health teams traced 77 contacts on day one: 2 highest-risk, 13 high-risk and 62 low-risk persons; the largest share were healthcare workers.
- Highest- and high-risk groups were quarantined; samples from five primary contacts were sent for testing; no second human case at the point of confirmation.
- The case was reported to the Centre and a district control room was opened.
The development matters in the context of:
- Zoonotic spillover and emerging infectious diseases with epidemic potential.
- Public-health surveillance, the One Health framework and India’s pandemic-preparedness architecture.
- Kozhikode recurring as the same hotspot, raising the question of whether Kerala’s response is a national model or a recurring alarm.
UPSC Relevance
Prelims Relevance
- Nipah virus (NiV) belongs to genus Henipavirus, family Paramyxoviridae (same broad family as measles and mumps).
- Natural reservoir: fruit bat, Pteropus species (flying foxes), in which the virus circulates without making bats ill.
- Classified BSL-4 (Biosafety Level 4) pathogen because of lethality and no licensed vaccine.
- WHO case-fatality rate: roughly 40-75 percent; listed among priority pathogens with epidemic potential.
- NIV Pune (under ICMR) is India’s apex reference lab for Nipah confirmation.
- India’s first Nipah outbreak: Perambra, Kozhikode district, Kerala, May 2018.
- First identified in the 1998-99 Malaysia-Singapore outbreak; named after Sungai Nipah village.
- Incubation period: typically 4 to 14 days, occasionally longer.
- No licensed vaccine; care is supportive, with monoclonal antibodies in trials.
- 21 people died of Nipah in Kerala between 2018 and 2024; the 2026 West Bengal cluster was India’s first outside Kerala.
Mains Relevance
GS Paper 3 (Science and Technology, Disaster Management):
- Nipah as a textbook emerging infectious disease and epidemic-potential pathogen with no cure.
- The One Health approach linking human, animal and environmental health to anticipate spillover.
- India’s wider pandemic-preparedness architecture: NCDC, IDSP, state rapid-response teams.
- State health-system capacity, surveillance speed and rapid diagnostics versus reliance on cure.
GS Paper 4 (Ethics):
- Protection of frontline healthcare workers as the most-exposed group during outbreaks.
- Balancing containment measures with civil liberties.
Essay: development-versus-conservation tension and how India shares space with its wildlife.
Background and Context
The Pathogen and Its Biology
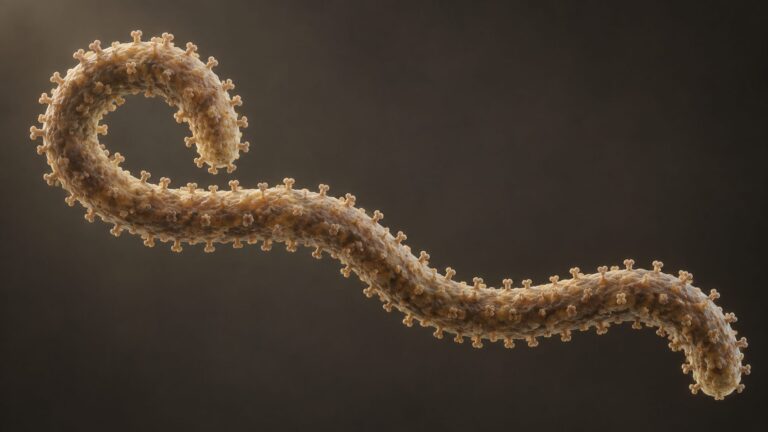
Nipah is a zoonotic RNA virus that normally lives in animals and spills over into humans.
- Genus Henipavirus, family Paramyxoviridae; handled only in BSL-4 facilities.
- WHO lists it among priority pathogens; case-fatality rate roughly 40-75 percent, far above most viral fevers.
- Natural reservoir is the fruit bat (Pteropus), which carries the virus without illness.
Routes of Spillover
- Contact with infected bats or their secretions, including fruit or raw date-palm sap contaminated by bat saliva or urine (the classic Bangladesh route).
- Contact with intermediate hosts such as pigs, which drove the original 1998-99 Malaysia-Singapore outbreak.
- Human-to-human transmission through close contact with a patient’s body fluids, making caregivers and healthcare workers the most exposed group.
Kerala’s Outbreak History
- First Indian outbreak began at Perambra, Kozhikode, in May 2018; nurse Lini Puthussery died after caring for early patients.
- Single-case spillovers in Ernakulam (2019) and Pazhur, Kozhikode (2021).
- 2023 Kozhikode cluster: six cases, two deaths; 2024 saw two further single cases.
- 21 deaths in Kerala between 2018 and 2024; repeated spillover in the same forested, bat-rich northern belt.
What Just Happened: The Diagnostic Trap
- The index patient first sought care around mid-May with fever that subsided and returned, moving through several facilities.
- High fever with confusion and behavioural change was first read as alcohol-withdrawal — the classic Nipah diagnostic trap, since early encephalitis mimics common conditions.
- After the Medical College lab flagged a positive, samples went to NIV Pune, which confirmed Nipah on 11 June.
- The patient was shifted to a dedicated isolation ward around midnight; the SDS block was sealed and parking suspended.
Key Features of the Containment Protocol
- Early lab confirmation: local Medical College test plus NIV Pune confirmation, sometimes aided by mobile BSL-3 field labs to cut turnaround.
- Contact tracing and route maps: reconstructing patient movements (here, a de-addiction centre widened the list) — treated as a living document.
- Risk stratification: contacts sorted into highest-, high- and low-risk so quarantine and testing focus where transmission is likeliest.
- Containment zones: masking and distancing advisories for Ramanattukara municipality.
- Isolation and PPE: dedicated wards and protective gear activated alongside isolation, because hospitals amplify Nipah fastest.
- One Health surveillance: bat sampling, fruit-handling advisories and animal-health coordination to find the spillover source.
Institutional Anchors
- NIV Pune (under ICMR): apex lab for the most dangerous human viruses; without it states cannot officially confirm Nipah.
- The 2018 response drove deployment of rapidly relocatable field laboratories closer to outbreak sites.
- One Health framework: human, animal and environmental health managed together; Nipah is its textbook case.
- India’s response capacity also rests on NCDC, the Integrated Disease Surveillance Programme and state rapid-response teams — the COVID-19 machinery.
The Ecological and Equity Lens
- Northern Kerala keeps producing Nipah due to dense Pteropus colonies, fragmented forest edges and land-use change pushing bats and people together.
- Culling or clearing roosts is ecologically wrong and counter-productive: Pteropus bats are keystone pollinators and seed-dispersers, and disturbance can increase viral shedding.
- The person at the front of a Nipah outbreak is often a manual worker; the most exposed once a case reaches hospital are nurses and junior staff.
- India’s structural gap is the missing vaccine and therapy; ICMR is backing domestic monoclonal-antibody development against Nipah.
- The 2026 Nipah outbreak in West Bengal — India’s first cluster outside Kerala — warned that other states may face spillover without Kerala’s reflexes.
Challenges and Concerns
- Diagnostic delay: early Nipah mimics common fevers, costing crucial containment time.
- Healthcare-worker exposure: hospitals are the main amplifier, as the 2018 death of nurse Lini Puthussery showed.
- Capacity asymmetry: Kerala’s system is strong, but the West Bengal cluster shows other states may lack the surveillance and reflexes.
- No vaccine or licensed therapy: response stays reactive, dependent on detection speed rather than a cure.
- Ecological drivers persist: habitat fragmentation and the human-bat interface mean spillover risk recurs each season.
Way Forward
- Strengthen year-round bat and fruit-handling surveillance under One Health so spillover is anticipated, not just reacted to, in known hotspot districts.
- Pre-position mobile BSL-3 field laboratories and standard diagnostic algorithms so encephalitis cases in high-risk belts are screened for Nipah early, cutting diagnostic delay.
- Manage the human-animal interface: keep date-palm sap and fruit out of contact with bat secretions, secure old buildings and orchards in hotspot districts.
- Accelerate and stockpile India’s monoclonal-antibody and vaccine candidates to move from containment alone toward treatment.
- Extend Kerala’s protocol and training to states with weaker surveillance, and protect frontline workers with PPE, training and recognition.
Conclusion
The 2026 Kozhikode case is a live audit of whether the lessons of 2018 and the pandemic have hardened into routine practice. Kerala’s speed — confirmation, isolation, 77 contacts traced and risk-stratified, and a control room within hours — is the dividend of institutional memory.
But the model rests on a strong public-health system that cannot be assumed across India. Against a virus with a 40-75 percent fatality rate and no cure, the country’s only defence is detection speed and the discipline of contact tracing — a thin margin.
The honest takeaway is that India contains Nipah well but cannot yet treat it, and that the durable fix is ecological: how the country shares space with its wildlife and protects the workers at the front line.
UPSC Practice Questions
Prelims MCQ 1
Consider the following statements regarding the Nipah virus:
- It belongs to the genus Henipavirus in the family Paramyxoviridae.
- Its natural reservoir is the fruit bat of the Pteropus genus.
- It is classified as a Biosafety Level 4 (BSL-4) pathogen.
- A licensed vaccine is available and is used widely in hotspot districts.
How many of the above statements are correct?
(a) Only two (b) Only three (c) All four (d) Only one
Answer: (b)
Explanation:
- Statements 1, 2 and 3 are correct: Nipah is a Henipavirus (Paramyxoviridae), its reservoir is the Pteropus fruit bat, and it is a BSL-4 pathogen.
- Statement 4 is incorrect: there is no licensed Nipah vaccine; care is supportive, with monoclonal antibodies still in trials.
Prelims MCQ 2
Which of the following institutions provides the confirmatory test that officially declares a Nipah outbreak in India?
(a) National Centre for Disease Control, Delhi (b) National Institute of Virology, Pune (c) All India Institute of Medical Sciences, Delhi (d) Indian Institute of Science, Bengaluru
Answer: (b)
NIV Pune, under ICMR, is India’s apex reference laboratory for high-risk viruses and provides the confirmatory test that turns a suspected case into a declared Nipah outbreak.
UPSC Mains Questions
1. Recurrent Nipah outbreaks in Kerala point to an ecological problem, not merely a medical one. Discuss the drivers of zoonotic spillover in India and the policy response required. (GS Paper 3, 15 marks, 250 words)
2. Examine how the One Health approach can strengthen India’s preparedness against emerging zoonotic diseases such as Nipah, and discuss the state’s obligations towards frontline healthcare workers during such outbreaks. (GS Paper 3, 10 marks, 150 words)
What is Nipah virus and why is it dangerous?
Nipah is a zoonotic virus of the Henipavirus genus that spreads from fruit bats to humans and then between people. It causes fever and encephalitis, has no licensed vaccine, and is handled only in BSL-4 labs. The WHO puts its case-fatality rate at roughly 40 to 75 percent, which is why even a single case triggers a full outbreak response.
How did the 2026 Kozhikode patient get infected?
The 43-year-old man from Ramanattukara worked cleaning old buildings and is suspected to have caught the virus while clearing a disused structure with a heavy bat presence near Feroke. This matches the classic spillover route, contact with fruit bats or their secretions, that drives most Indian Nipah cases.
How does Kerala contain a Nipah outbreak?
Kerala confirms the case at NIV Pune, isolates the patient, declares a containment zone, and reconstructs a route map to trace every contact. Contacts are sorted into highest-, high- and low-risk groups, with the riskier ones quarantined and tested. Speed and disciplined contact tracing are the core of the model.
Why does Nipah keep returning to Kozhikode?
Northern Kerala has dense Pteropus bat colonies and a fragmented forest edge where bats and people share space. Land-use change brings orchards, old buildings and settlements into that interface. The driver is ecological, so the same belt keeps producing spillover unless habitat and reservoir surveillance improve.
Is there a vaccine or cure for Nipah?
No licensed Nipah vaccine or proven antiviral exists yet. Treatment is supportive care, and the main specific tool, a monoclonal antibody, is still in trials. India’s ICMR is backing domestic monoclonal-antibody development. Until such tools are ready, the country’s real defence is fast detection and rigorous contact tracing.
What does the West Bengal cluster mean for India?
The 2026 West Bengal episode was India’s first Nipah cluster outside Kerala, and it showed that spillover is no longer geographically contained. Other states may face Nipah without Kerala’s trained surveillance and reflexes. The lesson is to extend the outbreak playbook and One Health surveillance nationwide before, not after, the next case.
Tell Google you want more of this.
Add Anantam IAS as a preferred sourceOne tap, and this site shows up more often in your own Top Stories, AI Overviews and AI Mode. Remove it any time.