Why in News?
India’s drug regulator has reportedly approved Qdenga, a live-attenuated tetravalent dengue vaccine made by Takeda, for people aged 4–60 years. It is being described as India’s first approved dengue vaccine.
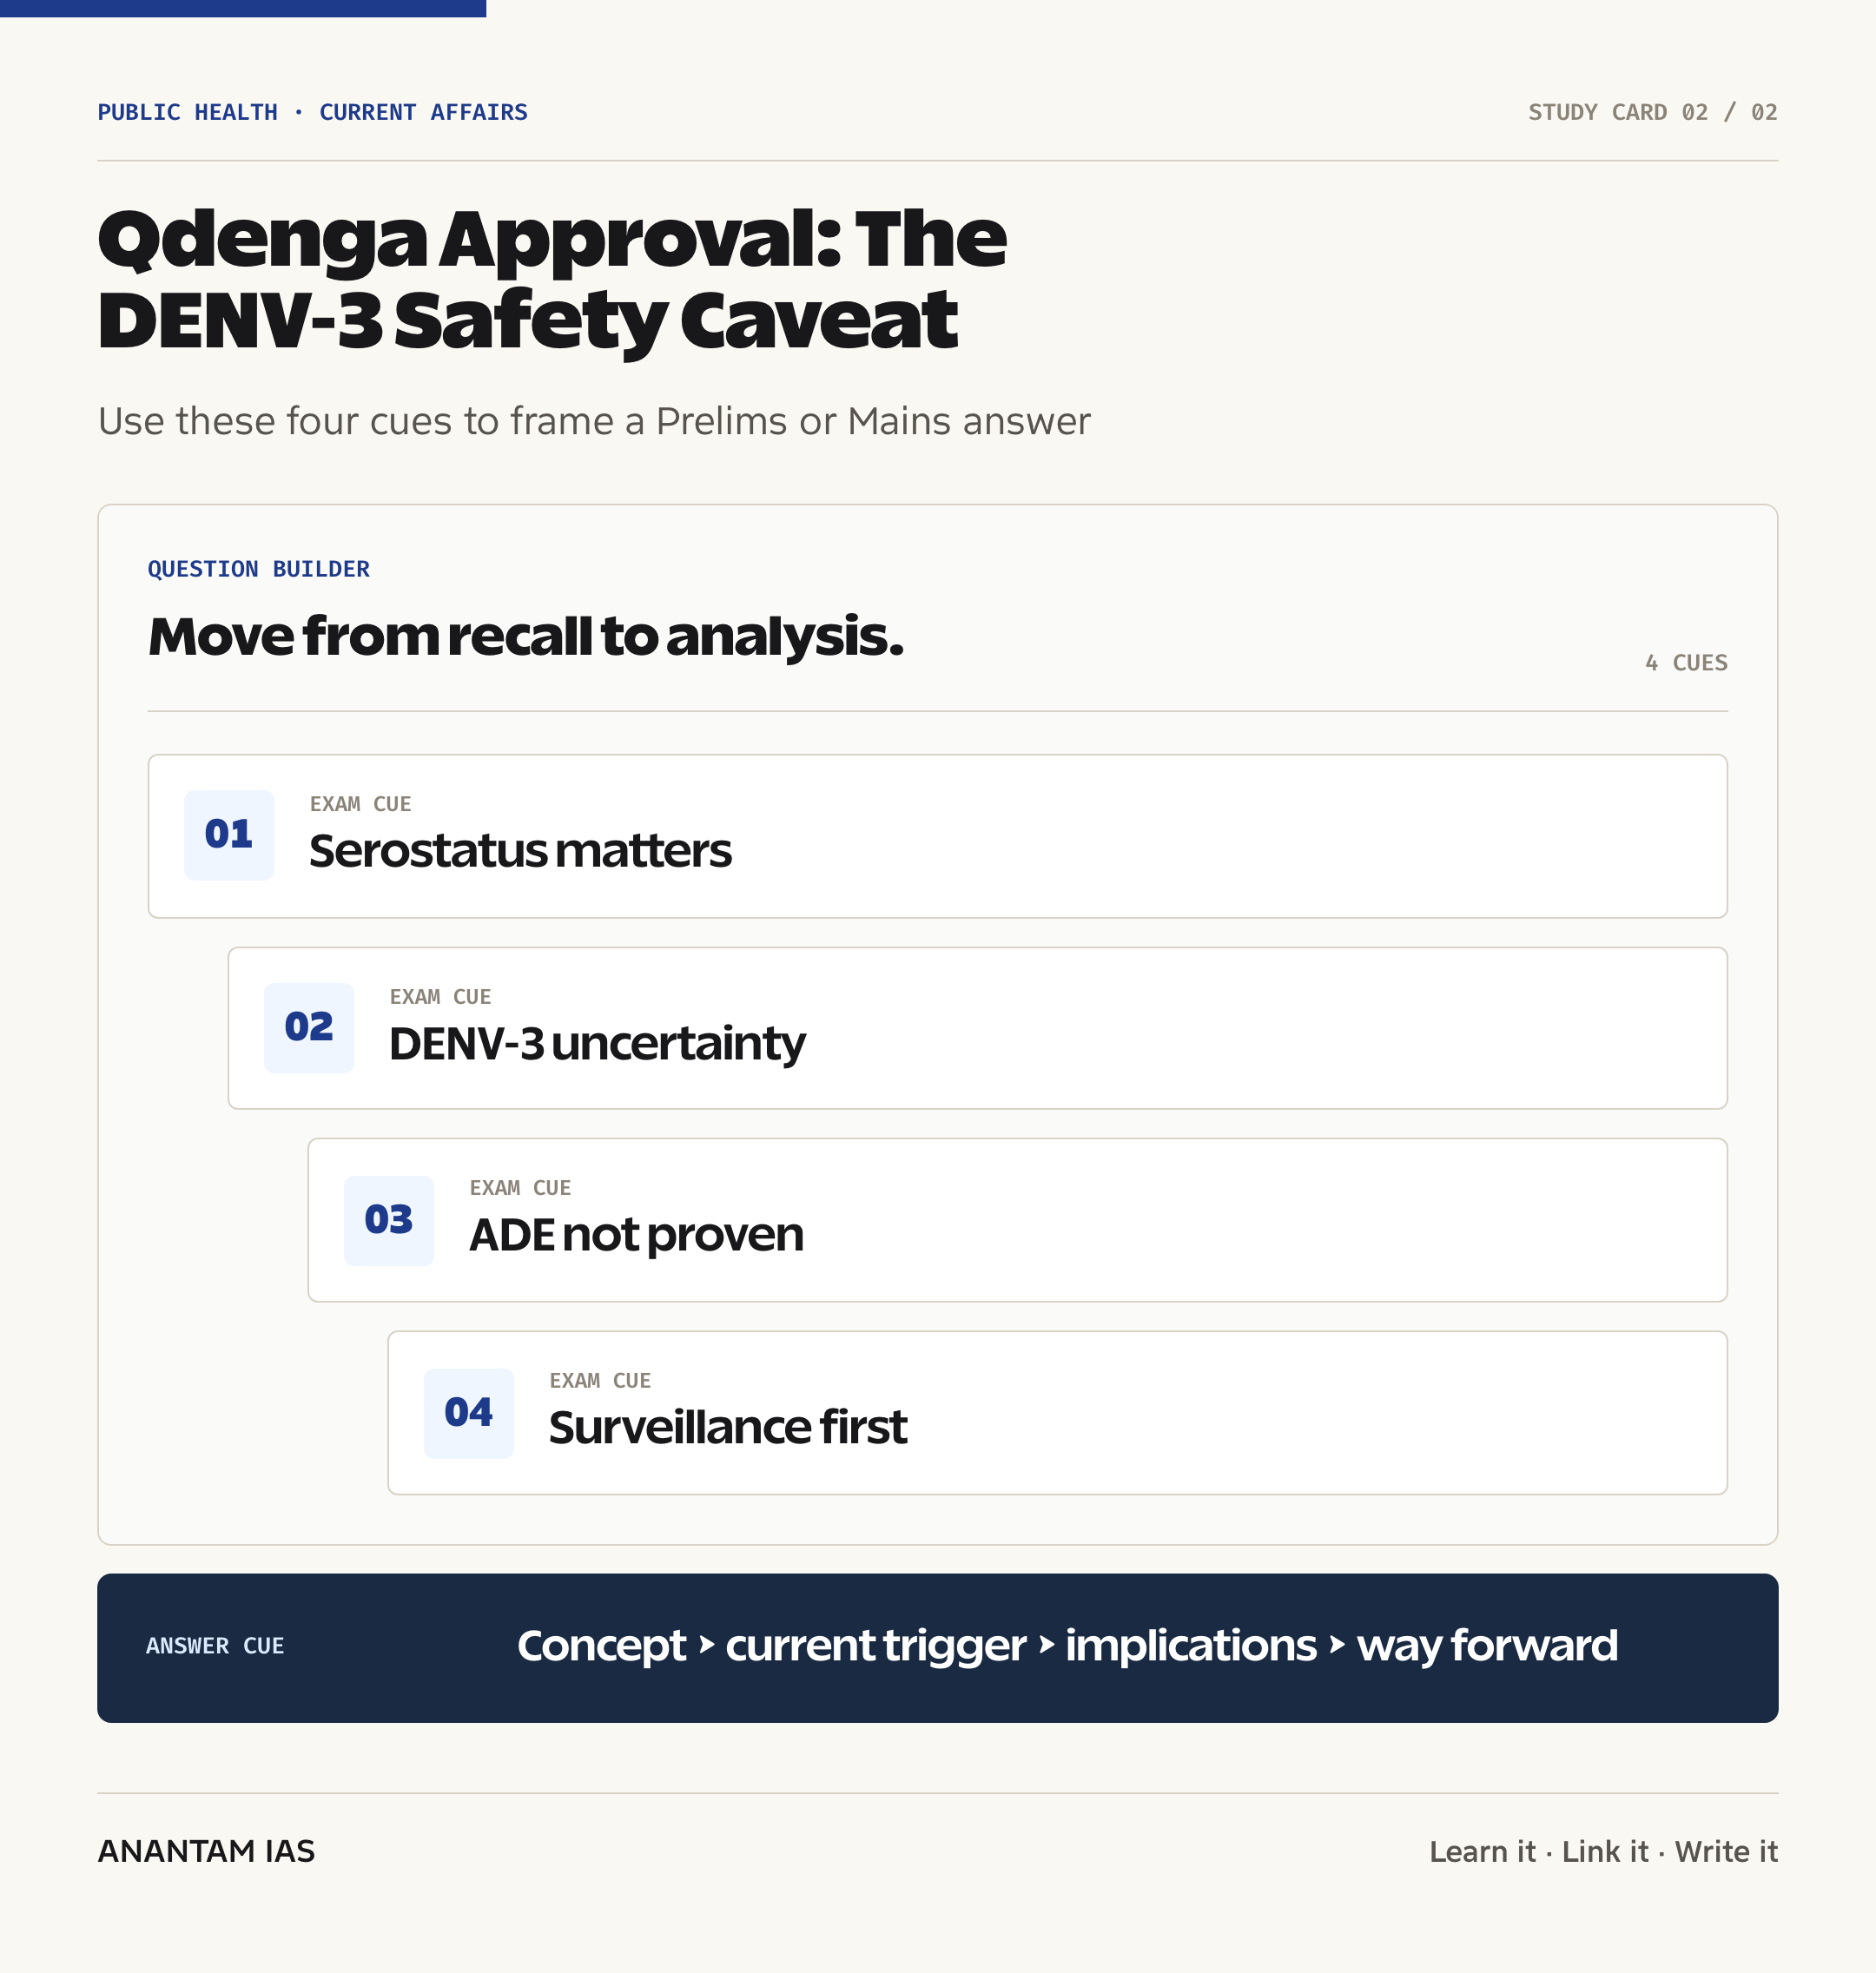
The approval has renewed scrutiny of the DENV-3 trial signal among children who were seronegative before vaccination. The available evidence doesn’t establish vaccine-enhanced disease, but it also doesn’t demonstrate protection against DENV-3 in this subgroup.
- The CDSCO Subject Expert Committee recommended import permission in March 2026 after reviewing the complete Indian Phase III report.
- The Indian study enrolled 480 healthy participants aged 4–60 and assessed safety and immunogenicity; it wasn’t designed as a large clinical-efficacy trial.
- The committee required a post-marketing safety and effectiveness study in Indians within six months of market introduction.
- The Hindu highlighted the unresolved question of DENV-3 protection in baseline-seronegative children and the biological concern of antibody-dependent enhancement.
- The public CDSCO minutes record an expert recommendation; the reported final approval is a later regulatory step and shouldn’t be confused with the committee’s advice.
The development matters in the context of:
- This matters in the context of India’s recurrent dengue burden and the need to add vaccines without weakening Aedes mosquito control and clinical surveillance.
- It also tests how regulators communicate subgroup uncertainty when a vaccine’s overall benefit can coexist with weak serotype-specific evidence.
- The issue links clinical-trial interpretation with pharmacovigilance, informed consent and evidence-based design of a future public immunisation programme.

UPSC Relevance
Prelims Relevance
- Dengue virus has four antigenically distinct serotypes: DENV-1, DENV-2, DENV-3 and DENV-4.
- Qdenga or TAK-003 is a live-attenuated tetravalent vaccine administered as two subcutaneous doses three months apart.
- A seropositive person has evidence of prior dengue exposure; a seronegative person lacks such baseline antibodies.
- Antibody-dependent enhancement is a mechanism in which non-neutralising antibodies may facilitate infection and contribute to severe disease during a later heterologous-serotype infection.
- The pivotal DEN-301 trial enrolled 20,099 children aged 4–16 across 26 sites in eight dengue-endemic countries.
- The World Health Organization recommends programmatic use of TAK-003 mainly for children aged 6–16 in settings with high dengue-transmission intensity.
- WHO’s recommendation doesn’t require routine pre-vaccination screening, but national policy may consider local epidemiology, test performance, feasibility and equity.
- The CDSCO regulates drugs and vaccines in India under the Union Ministry of Health and Family Welfare.
- Approval, trial evidence, WHO prequalification and inclusion in a national immunisation programme are distinct decisions.
Mains Relevance
GS Paper 3
- Interpretation of clinical-trial evidence by baseline serostatus and virus serotype.
- Vaccine biotechnology, pharmacovigilance and management of low-certainty safety signals.
- Integrated dengue control combining vaccination, surveillance, diagnostics and vector management.
GS Paper 2
- Public-health regulation, transparent risk communication and informed consent.
- Centre–State coordination for sentinel surveillance and adverse-event reporting.
- Equity implications of screening, private-market access and possible public-programme introduction.
Essay
- Scientific progress is strongest when uncertainty is made visible rather than hidden.
- Public trust depends on institutions explaining both the benefits and limits of medical evidence.
Background and Context
What the Regulatory Record Shows
The Indian decision must be read as a sequence of regulatory steps rather than as one undifferentiated approval event.
- In August 2025, the SEC asked Takeda to submit the complete Indian Phase III report before further deliberation.
- On 19 March 2026, the committee reviewed the completed report and recommended grant of new-drug import permission for ages 4–60.
- The minutes say the Indian study of 480 participants found the vaccine tolerated, safe and immunogenic in the presented dataset.
- Safety and immunogenicity, meaning the ability to generate an immune response, aren’t equivalent to demonstrated protection against clinical disease.
- The global efficacy evidence came chiefly from DEN-301, while the Indian trial supplied bridging evidence across adults, adolescents and children.
- The committee attached a condition: Takeda should begin an Indian post-marketing safety and effectiveness study within six months of market introduction.
- Students should distinguish an SEC recommendation from the regulator’s final permission order, and both from a government decision to procure the vaccine for a public programme.
How Qdenga Works
Qdenga seeks to induce protection against all four dengue serotypes with weakened viral components.
- The vaccine is live attenuated: its viral components are weakened so they stimulate immunity without causing ordinary dengue disease in immunocompetent recipients.
- It is tetravalent, covering DENV-1, DENV-2, DENV-3 and DENV-4; the construct uses a DENV-2 backbone for the other serotype components.
- The standard course is two subcutaneous doses separated by three months.
- The EMA authorises Qdenga from age four, while WHO’s public-programme recommendation focuses on ages 6–16 in high-transmission settings.
- A broad product licence states who may receive a product under official guidance; it doesn’t mean every eligible person should be vaccinated without a national risk-benefit policy.
- As a live vaccine, it is contraindicated for some people with severe immunodeficiency, as well as during pregnancy and breastfeeding under current product information.
Why Serostatus Changes the Question
Prior dengue exposure affects how both natural infection and vaccination are interpreted.
- A person is baseline seropositive when antibodies indicate a previous dengue infection before vaccination; a baseline-seronegative person has no such evidence.
- In natural dengue, infection by one serotype usually creates durable protection against that serotype but only temporary or incomplete cross-protection against the others.
- A later infection with a different serotype can carry a greater risk of severe disease, although severe outcomes depend on several host, viral and epidemiological factors.
- Antibody-dependent enhancement is one proposed mechanism: antibodies that bind but don’t neutralise a different serotype may help the virus enter immune cells.
- A dengue vaccine must ideally provide balanced protection, because weak protection against one serotype could leave a theoretical pathway for an infection resembling a secondary exposure.
- But a negative efficacy estimate isn’t proof of ADE. Demonstrating vaccine-enhanced disease requires consistent clinical, epidemiological and mechanistic evidence.
What the Global Trial Found
Overall results were favourable, but averages concealed important differences by serotype and baseline exposure.
- The pivotal trial randomised 20,099 children aged 4–16 in a roughly 2:1 vaccine-to-placebo ratio across eight endemic countries.
- Early trial results showed about 80% efficacy against virologically confirmed dengue and about 90% efficacy against hospitalisation over the principal follow-up window.
- Protection was strongest and most consistent against DENV-2; useful protection was also demonstrated against DENV-1.
- Among baseline-seropositive children, WHO’s evidence tables estimated DENV-3 efficacy of 52.3% against confirmed disease and 74.0% against hospitalised disease over 57 months.
- Among baseline-seronegative children, the point estimate against confirmed DENV-3 disease was −15.5%, with a very wide 95% confidence interval from −108.2% to 35.9%.
- For hospitalised DENV-3 in the same subgroup, the estimate was −87.9%, but it rested on only 14 cases and had a 95% confidence interval from −573.4% to 47.6%.
- Different hospital-admission practices, especially at Sri Lankan sites, added clinical heterogeneity; excluding Sri Lanka changed the point estimate substantially.
- The correct conclusion is limited: efficacy against DENV-3 wasn’t demonstrated in seronegative children, and a safety risk couldn’t be excluded. The trial didn’t prove increased risk.
WHO's Risk-Benefit Position
WHO supports targeted use where the expected population benefit is high, while acknowledging serotype-specific uncertainty.
- WHO recommends introduction of TAK-003 in children aged 6–16 in places where high transmission creates a substantial public-health problem.
- Countries should vaccinate about one to two years before the age-specific peak of dengue hospitalisation, using local surveillance to choose the target age.
- WHO doesn’t require routine pre-vaccination serological screening for this strategy, unlike the history of the earlier CYD-TDV vaccine.
- The position paper says no protection against DENV-3 and DENV-4 has been documented in seronegative recipients and available data can’t exclude increased hospitalisation or severe-dengue risk.
- At the same time, WHO judged that benefits substantially outweigh possible risks in high-transmission settings.
- This is a population-level recommendation, not a claim of uniform protection for every serotype, age or epidemiological setting.
Screening Debate and Policy Trade-offs
Screening may appear precautionary, but its public-health value depends on test accuracy and implementation.
- Advocates of screening argue that identifying seronegative children could reduce exposure of the subgroup with uncertain DENV-3 protection.
- A false-positive result could label a truly seronegative child as previously exposed and lead to vaccination; a false-negative could deny a potentially beneficial vaccine.
- Laboratory assays may show cross-reactivity with other flaviviruses or vary by time since infection, which complicates mass screening.
- Screening raises costs, access barriers and delay, potentially favouring urban families with better laboratory access.
- A no-screening strategy may be rational in areas of demonstrably high transmission, while a targeted-screening approach could be examined in lower-transmission or uncertain settings.
- India needs age- and district-specific seroprevalence, circulating-serotype data and validated tests before treating either strategy as universally correct.
Why Vaccination Cannot Stand Alone
Even an effective vaccine doesn’t remove the need for conventional dengue prevention and rapid care.
- Breakthrough infection remains possible, so vaccination can’t replace Aedes aegypti source reduction, larval control and household protection.
- DENV serotypes vary by place and season; genomic and serotype surveillance should be linked to hospital and vaccine-effectiveness data.
- Clinical services still need early recognition of warning signs, rational fluid management and referral pathways for severe dengue.
- India should integrate vaccination data with the Integrated Disease Surveillance Programme and adverse-event reporting systems.
- The distinct safety questions around Qdenga and India’s indigenous DengiAll programme shouldn’t be conflated; each product needs its own evidence review.
- For the wider regulatory background, compare this development with the earlier Qdenga approval note.
Way Forward
Publish a transparent Indian label
- State the approved ages, dose schedule, contraindications and evidence limits for baseline-seronegative recipients in plain language.
- Publish the final regulatory order and the rationale linking the Indian bridging study to global efficacy data.
- Keep product licensing separate from any later decision on public procurement or universal recommendation.
Build active post-marketing surveillance
- Begin the SEC-mandated study within the prescribed six-month window and pre-register outcomes and analysis plans.
- Track breakthrough cases by age, baseline serostatus where available, vaccine dose, infecting serotype, severity and hospitalisation.
- Use independent safety review and publish periodic findings, including null or reassuring results.
Design a context-specific rollout
- Pilot vaccination in high-burden districts with strong laboratory and hospital surveillance before wider expansion.
- Evaluate screening using Indian test-performance data rather than assuming that a theoretically cautious step is operationally safer.
- Ensure consent materials explain known benefits, unresolved uncertainty and the continued need for mosquito control.
Strengthen the evidence base
- Fund Indian effectiveness studies large enough to examine DENV-3 and DENV-4 outcomes, not only overall dengue.
- Maintain serotype and genomic surveillance so changes in circulating viruses can be linked to vaccine performance.
- Coordinate CDSCO, ICMR, the National Centre for Disease Control, States and independent experts through a public risk-management plan.
Conclusion
Qdenga gives India a new tool against a large and recurrent disease burden. Its overall efficacy and global use support cautious optimism, but population averages can’t erase the unresolved DENV-3 evidence in seronegative children.
A credible rollout should neither amplify an unproven harm nor dismiss a genuine uncertainty. Transparent labelling, local epidemiology, active surveillance and integrated vector control are the route from regulatory approval to responsible public-health use.
UPSC Practice Questions
Prelims MCQ 1
With reference to Qdenga, consider the following statements:
- It is a live-attenuated tetravalent dengue vaccine.
- Its standard course consists of two doses three months apart.
- WHO recommends its routine use in every country regardless of dengue transmission.
How many of the above statements are correct?
(a) Only one (b) Only two (c) All three (d) None
Answer: (b) Only two
Explanation:
Statements 1 and 2 are correct. WHO’s programme recommendation targets children in settings where high dengue transmission creates a substantial public-health problem; it isn’t a universal recommendation for every country.
Prelims MCQ 2
Antibody-dependent enhancement in dengue most accurately refers to:
(a) Antibodies directly destroying mosquito larvae (b) Non-neutralising antibodies facilitating infection by another serotype (c) A vaccine producing antibodies only after natural infection (d) Antivirals preventing antibody formation
Answer: (b) Non-neutralising antibodies facilitating infection by another serotype
Explanation:
ADE is a proposed mechanism in which binding but insufficiently neutralising antibodies can facilitate viral entry into immune cells. It is relevant to secondary heterologous dengue infection, but a negative efficacy estimate alone doesn’t prove ADE.
UPSC Mains Questions
- India’s reported approval of Qdenga combines a major preventive opportunity with unresolved serotype-specific evidence. Discuss how regulators should balance overall vaccine benefit, subgroup uncertainty, informed consent and post-marketing surveillance while designing a dengue vaccination strategy.
- Why can overall vaccine efficacy conceal important public-health risks or uncertainties? Explain with reference to baseline serostatus, DENV serotypes and confidence intervals in the Qdenga evidence, and suggest principles for responsible interpretation of clinical trials.
- Vaccination cannot substitute for integrated vector management in dengue control. Examine the institutional measures India needs to combine vaccination, serotype surveillance, adverse-event reporting, community communication and timely clinical management.
Sources: CDSCO Subject Expert Committee and WHO Position Paper on Dengue Vaccines.
Frequently Asked Questions
What is Qdenga?
Qdenga, also called TAK-003, is a live-attenuated tetravalent vaccine made by Takeda to prevent dengue caused by four virus serotypes. The standard schedule is two subcutaneous doses three months apart. Its use must follow the approved product label and public-health recommendations.
Who is seronegative for dengue?
A baseline-seronegative person has no detectable evidence of prior dengue exposure before vaccination. This status matters because Qdenga’s efficacy varied by baseline serostatus and serotype. WHO found no demonstrated protection against DENV-3 in seronegative children in the available Phase III evidence.
Does Qdenga cause antibody-dependent enhancement?
The available trial evidence doesn’t prove that Qdenga causes antibody-dependent enhancement. Negative DENV-3 efficacy estimates and case imbalances in seronegative children create a safety uncertainty, but the estimates are based on few cases and wide confidence intervals. A risk couldn’t be excluded.
What did the Indian trial establish?
The Indian Phase III study reviewed by the CDSCO expert committee enrolled 480 healthy people aged 4–60. The committee reported that the vaccine was tolerated, safe and immunogenic in the presented data. Global DEN-301 evidence, not this small Indian bridging study, supplied the main clinical-efficacy evidence.
Does WHO require screening before Qdenga?
WHO’s 2024 position doesn’t require pre-vaccination screening for its recommended use in children aged 6–16 in high-transmission settings. Screening remains a policy debate because it may identify prior exposure, but test errors, cost, access and local transmission can change its net value.
What should India monitor after rollout?
India should track breakthrough dengue by age, dose, baseline serostatus where feasible, infecting serotype, severity and hospitalisation. Active surveillance should especially examine DENV-3 and DENV-4 outcomes in seronegative recipients, alongside adverse events, circulating serotypes and real-world vaccine effectiveness.
Tell Google you want more of this.
Add Anantam IAS as a preferred sourceOne tap, and this site shows up more often in your own Top Stories, AI Overviews and AI Mode. Remove it any time.